HIPAA Compliance FAQ for Covered Entities and Business Associates
Plain answers to the HIPAA questions small practices and their vendors ask most: risk assessments, BAAs, written policies, staff training, and how to report an incident. For covered entities and business associates alike.
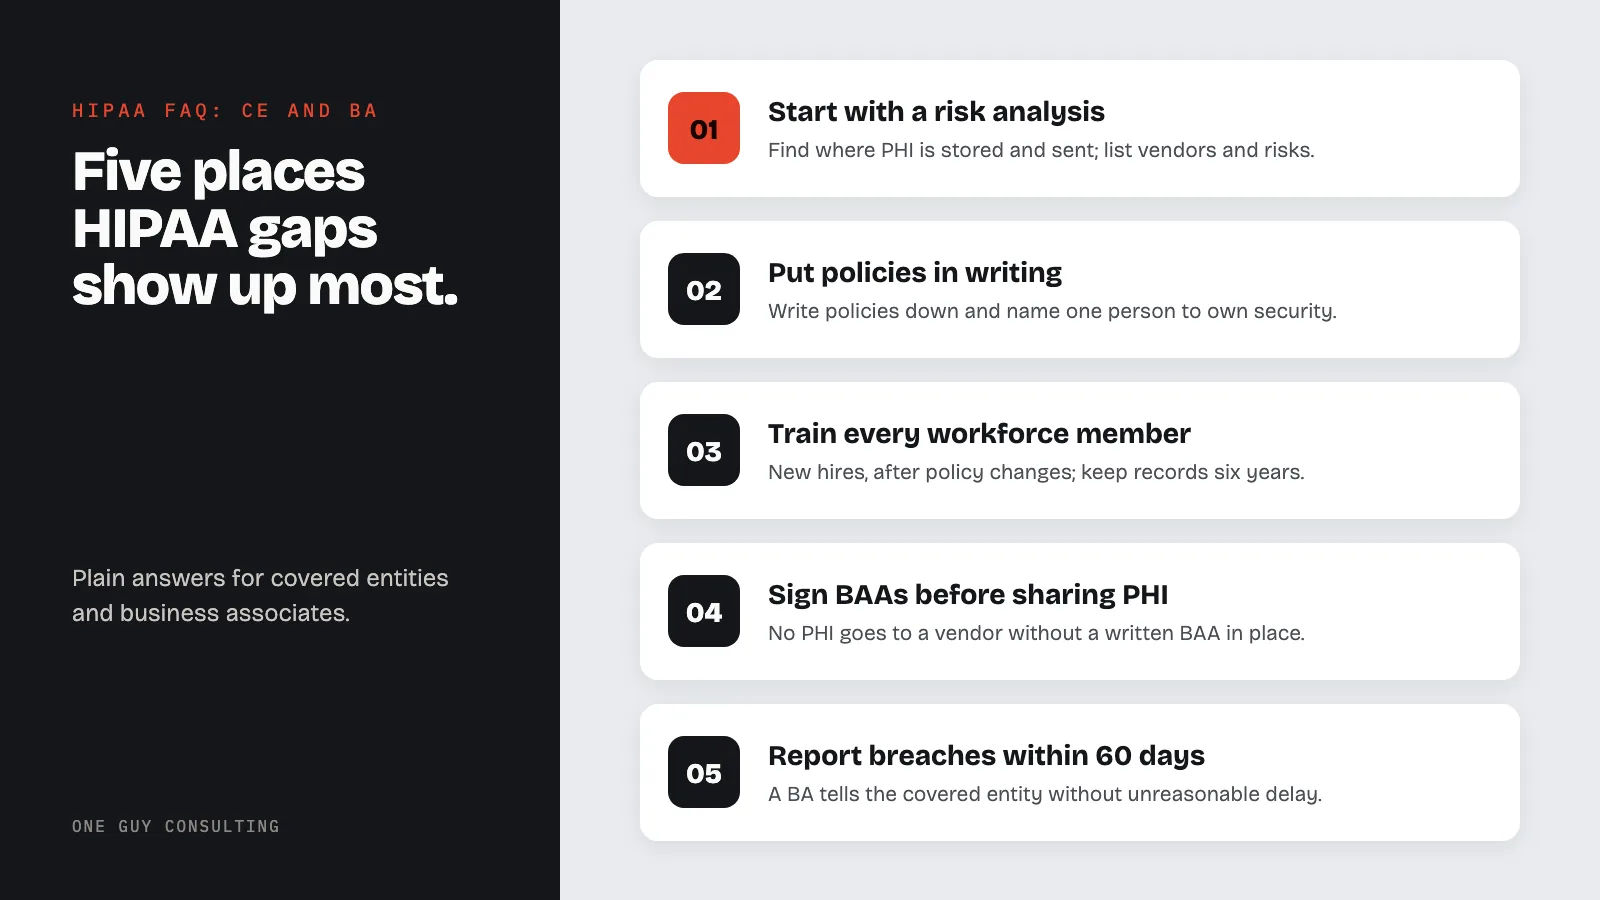
Overview
Run a small clinic? A dental office? A behavioral health practice? Or a firm that handles protected health information for a provider? The same HIPAA rules reach all of you. The questions below cover the spots where gaps show up most: Security Risk Assessments, written policies and procedures, workforce training, Business Associate Agreements, and incident reporting.
Who is this page for? A covered entity is a health care provider, a health plan, or a health care clearinghouse. A business associate is a firm or a person that creates, receives, maintains, or transmits protected health information (PHI) for a covered entity. Think IT vendors, billing services, cloud storage firms, and shredding companies.
HIPAA Compliance Questions and Answers
For covered entities: key duties and steps
3 questions01What HIPAA compliance help does One Guy Consulting offer for small healthcare practices?+
02Does HIPAA require staff training?+
03What happens if we don't have BAAs with our vendors?+
For business associates: duties and incident rules
2 questions04What HIPAA requirements apply to business associates?+
05What should a business associate do about incident reporting?+
Security Risk Assessments and next steps
3 questions06What is a Security Risk Assessment and is it required?+
07Does a business associate need its own Security Risk Assessment?+
08What do I do if my clinic has no HIPAA risk assessment or written policies?+
No questions match that search. Try a shorter word, check the glossary, or ask Chuck directly.
Covered entity vs. business associate: who owes what
Most of the Security Rule lands on both sides of the contract. The big difference is who you notify after a breach, and who you sign BAAs with. Here is the short version, with the rule each line comes from.
| Duty | Covered entity | Business associate | Rule (45 CFR) |
|---|---|---|---|
| Security Risk Analysis | Required | Required, and it must be its own; it cannot lean on the covered entity's | 164.308(a)(1)(ii)(A) |
| Security awareness and training | For all workforce members, management included | Same duty, same scope | 164.308(a)(5)(i) |
| Written security policies and procedures | Required | Required | 164.316(a) |
| Business Associate Agreements | With each business associate before it creates, receives, maintains, or transmits PHI | With each subcontractor that handles PHI on its behalf | 164.502(e), 164.308(b) |
| Breach notice | To each affected individual, without unreasonable delay and no later than 60 calendar days after discovery; also to HHS and, for a breach of more than 500 residents of a state, the media | To the covered entity, without unreasonable delay and no later than 60 calendar days after discovery | 164.404(b), 164.406, 164.408, 164.410(b) |
| Keep the paperwork | 6 years from the date it was created or last in effect, whichever is later | Same | 164.316(b)(2)(i) |
“A covered entity may disclose protected health information to a business associate and may allow a business associate to create, receive, maintain, or transmit protected health information on its behalf, if the covered entity obtains satisfactory assurance that the business associate will appropriately safeguard the information.”
That “satisfactory assurance” is not a handshake. Under 164.502(e)(2), it has to be written down in a contract or other written agreement that meets 164.504(e). In plain terms: the signed BAA.
What these gaps look like in real practices
These are anonymized results from practices I have worked with. Each one lines up with a duty covered above.
- Missing BAAs (Case 05). I worked with a single-location practice whose leaders were on board and whose staff was trained. In a wider review, we found several vendors touching PHI with no Business Associate Agreement in place. We built a full vendor list, sorted each vendor by how much PHI it could reach, got every missing BAA signed, and set up a vendor review the practice can run again. Read Case 05.
- No written policies (Case 01). A mental health franchise office in Florida called me with a state auditor due in days. Policies were never written, records had holes, and staff training was half done. We ran a fast gap analysis, built a ranked plan around what the auditor was most likely to ask for, and held a short check-in each day. The office was audit-ready in under a week and passed its state audit. Read Case 01.
- Low program take-up (Case 03). At a health group with more than 100 offices, take-up of the program swung wildly from office to office. I read the activity data, then reached out office by office, person to person. Take-up rose by about 17%. Read Case 03.
Key references and resources
- HHS OCR: HIPAA guidance for professionals
- HHS: Breach Notification Rule guidance
- OCR Breach Portal (HHS)
More anonymized results: all six case studies.
Learn More About HIPAA Compliance
One Guy Consulting in 37 seconds
Have a HIPAA Question This Page Did Not Cover?
Book a free 30-minute intro call. One Guy Consulting will look at where you stand and outline next steps, whether you are a covered entity or a business associate.