HIPAA applies to an OB/GYN practice because it bills electronically. A court struck down the 2024 reproductive health privacy rule nationwide on June 18, 2025. Now the base Privacy Rule and any stricter state law cover reproductive health information. Vendors that hold patient data for the practice need a Business Associate Agreement (a contract that obligates the vendor to safeguard that data). Labs do not.
Wednesday in an OB/GYN practice. A husband at the front desk asks what time his wife's appointment is and whether the results are in. A prenatal genetic screen posts to the portal before the physician has called. A seventeen-year-old asks about contraception and whether her mother will find out. A law firm's subpoena for a former patient's prenatal records sits in the fax tray. Every one of those is a Privacy Rule question, and in 2025 a federal court changed which version of the rule answers them.
The HHS Office for Civil Rights (OCR) enforcement listing shows the sector under scrutiny. OCR settled with Holy Redeemer Family Medicine over the disclosure of a patient's protected health information, including reproductive health information (November 2024). It entered a resolution agreement and corrective action plan with Regional Women's Health Group, LLC (August 2025). Years earlier, careless handling of HIV information cost an entity $387,200 (May 2017). Reproductive and sexual health information is the category where a single mishandled disclosure does the most damage to a patient.
Why HIPAA Applies to an OB/GYN Practice
45 CFR 160.103 defines a covered entity to include "a health care provider who transmits any health information in electronic form in connection with a transaction covered by this subchapter." An OB/GYN practice bills prenatal care, deliveries, procedures, and office visits electronically, so it is a covered entity. The same section defines health information as "any information, including genetic information," which matters in a specialty built on carrier screening and prenatal genetic testing; the definition of genetic information expressly includes "a fetus carried by the individual." The test is walked through in what is a covered entity under HIPAA.
The 2024 Reproductive Health Rule: Vacated, but Still Printed
In April 2024 HHS finalized a rule titled "HIPAA Privacy Rule to Support Reproductive Health Care Privacy." It added a prohibition on using or disclosing P.H.I. (Protected Health Information) to investigate or impose liability on a person for lawful reproductive health care, an attestation (a signed statement from the requester) requirement for certain requests, and three new Notice of Privacy Practices elements. On June 18, 2025, a federal district court in Texas, in Purl v. HHS, vacated (struck down) that rule nationwide. As of this writing the eCFR still displays the vacated text at 164.502(a)(5)(iii), 164.509, and 164.520(b)(1)(ii)(F) through (H).
What this means in practice: the base Privacy Rule governs reproductive health P.H.I. the same way it governs everything else. Disclosures for judicial proceedings run under 164.512(e), law enforcement disclosures under 164.512(f), and required-by-law disclosures under 164.512(a). The attestation form and the three notice elements are not required. What did survive from the same 2024 rulemaking is the set of notice changes tied to 42 CFR Part 2 substance use disorder records, with a compliance date of February 16, 2026; those apply only to a practice that creates or maintains Part 2 records, which is covered in 42 CFR Part 2 vs HIPAA.
State law is the other half of the answer. Under 45 CFR 160.203(b), a state law that "relates to the privacy of individually identifiable health information and is more stringent" than the federal Privacy Rule is not preempted, which means federal law does not override it. Several states have enacted their own reproductive health data protections since 2022. Which ones apply is a question for counsel, and the subpoena and law enforcement procedures should be written with that answer in hand.
What P.H.I. Looks Like in OB/GYN
- Prenatal records. Flowsheets, estimated due dates, visit notes, and the delivery summary shared with the hospital.
- Ultrasound images. Stored in an image archive or reporting system, often with a vendor's cloud component, and printed for the patient to take home.
- Fetal monitoring data. Non-stress test strips (fetal heart rate tracings) and surveillance records from in-office monitoring systems.
- Genetic screening results. Carrier screening (testing parents for conditions they could pass on), cell-free DNA screening (a maternal blood test for fetal chromosomal conditions), and diagnostic testing results that are genetic information about the patient and the fetus.
- Sexual health results. Pap and HPV results, sexually transmitted infection testing, and HIV status.
- Contraception and fertility records. Prescriptions, device placements, and fertility treatment cycles.
- Portal messages and reminders. A text that says "your prenatal visit is Thursday" discloses the pregnancy to whoever reads the phone.
- Designated-person forms. The list of people the patient has agreed may receive information, and the ones she has said may not.
Common Violations in OB/GYN Practices
The partner at the front desk. 45 CFR 164.510(b)(1)(i) permits disclosure to a family member, other relative, or a close personal friend of the individual
of P.H.I. directly relevant to such person's involvement with the individual's health care
, and 164.510(b)(2) conditions it on the patient's agreement, the opportunity to object, or a reasonable inference from the circumstances. A partner present in the exam room supports the inference for what is discussed while he is there. A partner at the front desk asking for results, appointment times, or whether a visit happened should get nothing unless the patient has said so. When she is not there, 164.510(b)(3) allows one narrow exception: the practice may share only what relates to the partner's role in her care, if professional judgment says that is in her best interest. That is not a front desk decision.
The workable fix is a designated-person form completed at intake and visible in the chart. The template is in the HIPAA release form.
Voicemails and mail to the wrong address. 164.522(b)(1)(i) requires the practice to accommodate reasonable requests by individuals to receive communications of protected health information ... by alternative means or at alternative locations
, and 164.522(b)(2)(iii) forbids requiring an explanation. In OB/GYN the request often comes from a patient whose pregnancy or test result is not safe to share at home. "Cell phone only, no voicemail, no mail" has to be honored the first time. The front desk mechanics are in HIPAA front desk rules.
Minors and parents. 164.502(g)(3)(i) makes a minor the "individual" for a service she may lawfully obtain without parental consent under state law, and 164.502(g)(3)(ii) defers to state law on whether a parent may be told. Which services qualify (contraception, sexually transmitted infection care, prenatal care) is a state-law question. The practice needs a written policy naming its state's rules, and a portal setup that does not hand a parent's proxy account the record of a confidential visit.
Subpoenas answered like records requests. 164.512(e)(1)(i) permits disclosure in response to "an order of a court or administrative tribunal," limited to what the order authorizes. A subpoena, discovery request, or other lawful process without a court order is different: under 164.512(e)(1)(ii) the practice may respond only after receiving "satisfactory assurance" that the requesting party made reasonable efforts to notify the patient, or to secure a qualified protective order. A subpoena for prenatal records that arrives by fax is not self-executing. It goes to the privacy official (the staff member in charge of privacy) and to counsel, and the response is logged.
Newborn photos and testimonials. A birth announcement on the practice's social media discloses P.H.I. of the patient and the newborn. 164.508(a)(1) requires a valid written authorization, meaning the patient's signed permission, before the practice uses or shares P.H.I. this way. She signs for herself and, as the newborn's personal representative, for the baby.
Results that reach the wrong person. A genetic screen posted to a shared family portal login, an HIV result faxed to the wrong number, or a Pap result read aloud to whoever answers the phone: each is an impermissible disclosure to be assessed under the breach definition at 164.402.
Building the Program
Risk analysis that includes imaging and monitoring. 164.308(a)(1)(ii)(A) requires "an accurate and thorough assessment of the potential risks and vulnerabilities" to ePHI (electronic P.H.I.). For OB/GYN that includes the ultrasound archive and any cloud reporting component, fetal monitoring systems and their vendor remote access, the portal and its proxy settings, and the reminder texting platform.
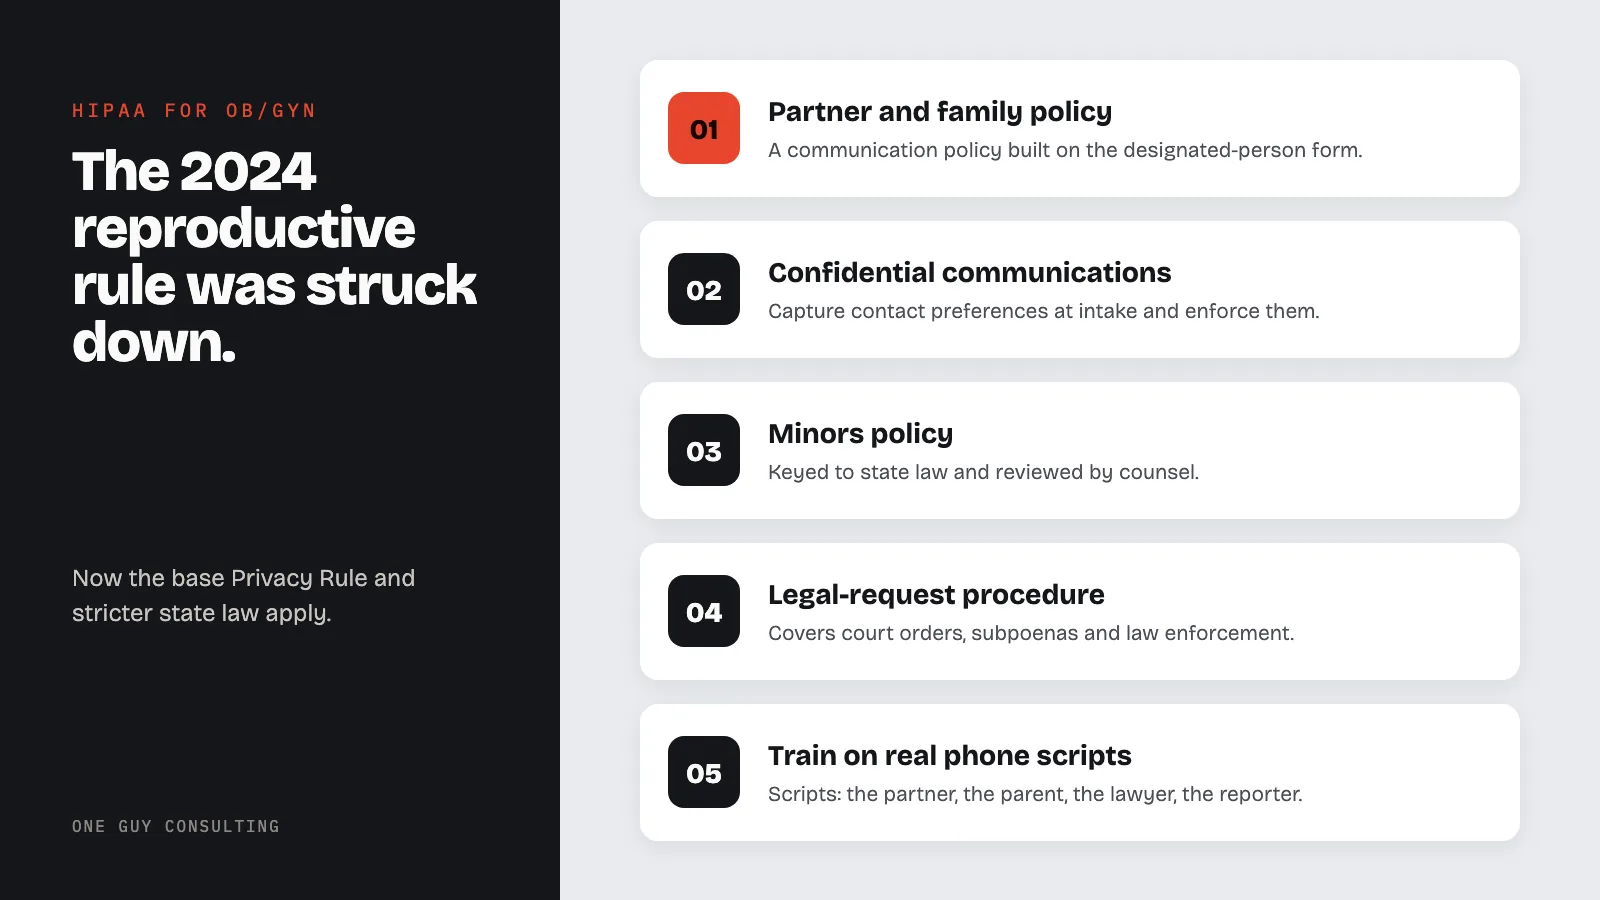
Four practice-specific policies. A partner and family communication policy built on the designated-person form; a confidential communications procedure that captures the patient's contact preferences at intake and enforces them; a minors policy keyed to state law and reviewed by counsel; and a legal-request procedure covering court orders, subpoenas, and law enforcement, with the 164.512(e) and (f) conditions written in.
Notice of Privacy Practices, reviewed. 164.520(c)(2) requires the notice at first service delivery with a good-faith effort to obtain acknowledgment. A notice review with counsel, rather than a rewrite, is the sensible step. The baseline content is in Notice of Privacy Practices: HIPAA NPP requirements.
Training on the phone call. 164.530(b)(1) requires training for all workforce members. The failures in this specialty happen at the front desk and on the phone, so the training uses the actual scripts: the partner, the parent, the lawyer, the reporter. Document it and keep the record for six years under 164.530(j)(2).
Vendor B.A.A. Checklist for OB/GYN
A business associate under 160.103 is a person who, on the practice's behalf, "creates, receives, maintains, or transmits protected health information" for a regulated function. The same definition excludes "a health care provider, with respect to disclosures by a covered entity to the health care provider concerning the treatment of the individual," which covers the labs and the hospital.
| Vendor category | Typical examples | B.A.A. required? |
|---|---|---|
| OB/GYN EHR and portal | athenahealth, eClinicalWorks, Epic Community Connect | Yes |
| Ultrasound reporting and image archive | Any cloud reporting or PACS (picture archiving and communication system) vendor holding images | Yes |
| Fetal monitoring and surveillance systems | Any system with vendor cloud storage or remote access | Yes, when the vendor can reach the data |
| Reminder, recall, and texting platform | Any patient messaging service | Yes |
| Telehealth and AI scribe or transcription | Any video visit or documentation vendor | Yes |
| Billing company, IT managed services, cloud fax, shredding | The standard back-office vendors | Yes |
| Genetic testing and clinical laboratories | The labs receiving specimens | No. The lab is a health care provider receiving P.H.I. for treatment and is a covered entity itself. |
| Hospital labor and delivery, mammography center, maternal-fetal medicine consultants | Providers the practice coordinates care with | No, for treatment disclosures |
| Pregnancy and cycle-tracking apps suggested to patients | Consumer apps the patient downloads herself | No B.A.A.; the app is not acting for the practice. Patients should know the app is outside HIPAA unless the practice contracts for it. |
| Public health reporting | State birth, disease, and cancer registries | No. Disclosures run under 164.512(b) to a public health authority; document the basis. |
The Proposed Security Rule Update (Proposed, Not Final)
HHS published a Notice of Proposed Rulemaking (a draft rule) on January 6, 2025 that would make encryption and multifactor authentication required rather than addressable. It is proposed, not final, and OCR is not enforcing it (HIPAA Security Rule delayed to 2027). Encrypting the ultrasound archive and turning on multifactor authentication for the portal are worth doing now, because those systems hold the information patients most fear seeing exposed.
FAQ
Does the 2024 reproductive health privacy rule still apply?
No. A federal district court vacated the April 2024 rule nationwide on June 18, 2025, in Purl v. HHS. Even though the eCFR still prints it, the base Privacy Rule and any more stringent state law now govern reproductive health information.
Can the front desk tell a husband or partner about his wife's appointment or results?
If the patient is there, only if she agreed, had a chance to object and did not, or the situation reasonably shows she does not object (45 CFR 164.510(b)(2)). If she is not there, 164.510(b)(3) allows a narrow professional-judgment exception, which is not a front desk decision. Without a designated-person form on file, the answer at the desk is no.
Can a minor's OB/GYN visit be kept from her parents?
It depends on state law. Under 164.502(g)(3), a minor who may lawfully consent to a service alone is the individual for that information, and state law decides whether a parent may be told. Write that into policy and into the portal setup.
Does the practice need a BAA with its genetic testing lab?
No. The lab is a health care provider receiving specimens for treatment, which 160.103 excludes from the business associate definition. The practice still sends only what the lab needs.
What should the practice do with a subpoena for prenatal records?
Route it to the privacy official and counsel. Under 164.512(e), a court order permits disclosure of only what it authorizes. A subpoena without a court order first needs satisfactory assurance: proof of reasonable efforts to notify the patient or to get a qualified protective order (a court order that limits use of the records to that case). State law may add conditions.
An OB/GYN practice needs a written answer to three questions before the next phone call: who the patient has designated, how the practice responds to a subpoena, and what the current rule actually requires now that the 2024 amendments are gone. One Guy Consulting's Full-Scope plan includes a Security Risk Assessment tool, policy and procedure templates, staff training, vendor management with digital B.A.A.s, and 4 hours a month of 1:1 implementation calls with Chuck. Start with a free 30-minute intro call. No obligation, no pressure.
One Guy Consulting in 37 seconds
Sources
- 45 CFR 160.103 (definitions)
- 45 CFR 160.203 (preemption)
- 45 CFR 164.502 (personal representatives)
- 45 CFR 164.508 (authorizations)
- 45 CFR 164.510 (family involvement)
- 45 CFR 164.512 (permitted disclosures)
- 45 CFR 164.520 (privacy notice)
- 45 CFR 164.522 (confidential communications)
- HHS OCR: Resolution Agreements
- Security Rule NPRM (January 6, 2025)
Related Reading: patient rights under HIPAA; HIPAA and social media.
Try three One Guy Consulting 3D staff training courses free →